
Hello.
We are Hanstep Korean Medicine Clinic, researching and treating ulcerative colitis since 2007.
Today I want to walk through a case where the symptoms were very severe.
This patient came to us in September 2023. A man in his seventies.
Ulcerative colitis usually develops in younger people, in their twenties and thirties. This patient developed it in his seventies, which is not common.
His symptoms began around May 2023 and he was diagnosed with ulcerative colitis.
He was already taking a long list of Western medications:
Azathioprine — an immunosuppressant. A drug that suppresses the immune system.
Prednisolone — a strong steroid.
An enteric-coated NSAID — a non-steroidal anti-inflammatory drug.
Esomeprazole — a gastric acid suppressant. When you take this many Western drugs, the stomach often suffers and starts burning, so this gets added on.
Folic acid — a vitamin B preparation.
And those are only the drugs related to his ulcerative colitis. Because of his age he was also taking medication for blood pressure, for cholesterol, for circulation, and more.
A whole handful of pills, every day.
The other medications are not my concern here. What matters is this: his symptoms began in May 2023, and even while staying on steroids, an immunosuppressant and anti-inflammatories, he was not improving.
That is why he came to Hanstep Korean Medicine Clinic.
Let’s look at his symptoms.
Bowel movements 6 to 7 times a day. That is a lot.
Loose stools, of course, with blood and mucus.
A sense of incomplete evacuation, along with urgency. He came to the clinic wearing an adult diaper.
When ulcerative colitis gets bad enough, the abdominal pain comes on suddenly and the signal to go arrives, and many patients cannot hold it for the one or two minutes it takes to reach a toilet.
They soil themselves in those one or two minutes.
For a grown adult this is genuinely distressing. You stop leaving the house. And if you absolutely have to go out, you go out wearing an adult diaper.
That weighs on a person.
He also could not pass gas on its own. Whenever gas came, he had to go to the toilet.
What does that mean? Patients with ulcerative colitis will understand immediately.
There are times when you want to pass gas. Normally you can shift to one side and let it out quietly.
But for a patient with ulcerative colitis, the moment the anus opens even slightly to release gas, discharge, blood and mucus spray out along with it.
So they cannot pass gas quietly at all. Every time gas comes, they have to go to the toilet and deal with it.
That alone becomes an enormous burden.
Now let’s look at his other symptoms.
Appetite normal. He ate a full portion. Digestion no problem at all.
I have said before that the most common type of ulcerative colitis patient is the one with accompanying digestive trouble.
The most common presentation is loss of appetite and poor digestion, together with abdominal pain, diarrhea and bloody stool.
But this patient had no digestive problem whatsoever. He was eating a full portion.
That is a different picture.
Should a patient whose digestion is fine be treated the same way as a patient whose digestion is poor?
No.
The prescription used for a patient with poor digestion will have no effect on this man. He needs a prescription written for abdominal pain, diarrhea and bloody stool in someone whose digestion is intact.
The details differ this much.
Mild swelling in the legs, sometimes in the afternoon. Not a significant problem.
Urination 5 to 6 times a day. Normal.
No rhinitis.
No particular coldness in the abdomen.
So: no rhinitis, no edema, no digestive trouble, no cold abdomen.
And yet there is a sense of incomplete evacuation. That is the symptom that has to be distinguished from the reduced-bowel-function type.
He also had a numb sensation along the gallbladder meridian in the left lower leg, and cold feet. Those are neurological symptoms, so acupuncture needed to be given alongside.
Then we ran a fecal calprotectin test, and the value came back at 12,361.

For a typical ulcerative colitis patient with some bloody stool and some diarrhea, calprotectin usually comes back somewhere between 1,000 and 3,000. Fifteen hundred, two thousand, that range.
This man came back at over 12,000.
Extremely high.
And the amount of blood in the stool was so great that it exceeded the measurable range — reported as over 1,200.
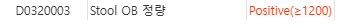
He had been on steroids and an immunosuppressant for more than four months, and his symptoms had not improved. No response at all.
The disease was severe.
We began treatment with herbal medicine immediately.
Normally we prepare two packs a day — one pack brewed from one dose, taken once in the morning and once in the evening, twice daily.
But this man’s symptoms were severe, and he wanted to improve quickly.
Understandably so. A grown adult having to put on a diaper every time he leaves the house — imagine how uncomfortable that is.
So we made an exception and increased it to three doses a day, three packs daily.
I have mentioned that I began treating ulcerative colitis and Crohn’s disease in 2007. In the early years I had patients take five doses a day, five times daily.
As my clinical experience deepened and my skill improved, I found that going that far was usually unnecessary, and that two doses a day was generally enough. So now I treat with two doses a day.
But in unusual situations like this one, I will still prescribe three or four doses a day.
This is one of the good things about herbal medicine. As long as the prescription is well chosen and suits the body, taking this much during the treatment period causes no problems at all. If anything, the illness resolves faster.
So for this patient we started strong, at three doses a day.
One month into treatment, by October, bowel movements had dropped to 4 or 5 times a day. The sense of incomplete evacuation had almost disappeared.
Blood and mucus in the stool, which had been constant before, were now only occasional — after one month of treatment.
The urgency had improved a great deal too. He said he could hold it now.
The hospital began tapering his steroid, reducing it by one tablet each week.
Two months in, by early November, bowel movements were down to 2 or 3 a day, with normal stools. No blood for a week.
Enormous improvement in two months.
When I start treatment I usually talk about aiming for roughly 50% improvement by the three-month mark. This patient was already 70 to 80% better in two months.
Then in December, the third month, bowel movements were still 2 to 3 a day. The steroid had been stopped. But he said blood was showing up very occasionally.
He had improved steadily right through November, and then in December the sense of improvement slowed.
This happens. You treat, the patient keeps getting better, and then at some point it starts to feel like a plateau.
You watch for a month or two, and if it really is a plateau, that is precisely the point where the prescription has to change.
Sometimes patients come to me for barely a month, see nothing dramatic, and get frustrated that all I say is “take the herbal medicine and let’s watch.”
Here is how it works.
Unlike Western medicine, we do not prescribe the same drug to everyone. When the symptoms are clear-cut, the very first prescription can be the right one, and then the effect shows immediately.
But some patients have ambiguous symptoms. Of course they do. In those cases the first prescription may be wrong. And then there is little effect.
When that happens, there are usually three or four candidate prescriptions, and you work through them in turn until you find the one that fits the patient.
Find it quickly and the effect comes quickly. Find it late and improvement takes longer.
That is why I say three months at the outset. And some people cannot wait even those three months. They come for a month or two and simply stop.
That does not work.
There is nothing I can do about it.
With this patient too, the effect was excellent at first, and then at some point it flattened out. Just about the same, week to week.
That is the moment to find the next prescription and move on. If a patient walks away mid-course because it feels like nothing is happening, it will not work out in the end.
So from January 2024 we changed the prescription and continued treatment.
Once the prescription changed, the symptoms started improving rapidly again. A patient can tell right away when this happens.
One month after the change, by February 2024:
Blood in the stool was gone again.
He could pass dry gas.
The urgency was gone.
He stopped the immunosuppressant, azathioprine.
A great deal better.
So on February 5 we ran another fecal calprotectin test. It came back at 54.

An enormous drop.
It had started at over 12,000. Now 54. Remarkable, isn’t it?
We continued treatment, and by April and May 2024:
Bowel movements twice a day, normal stools.
Blood and mucus long gone.
Able to pass dry gas.
No urgency.
He had been out of diapers for a good while.

April 12: fecal calprotectin 49.
May 22: fecal calprotectin below 3.8.
And with that we ended treatment.
I spoke with him by phone some time later, and he said he was doing fine, with no problems at all.
Today we looked at a case of severe ulcerative colitis in a man in his seventies, whose fecal inflammation marker was over 12,000.
A few things worth remembering.
Ulcerative colitis can develop in elderly patients too.
A patient who does not respond to steroids or immunosuppressants can still improve with herbal medicine.
In ulcerative colitis we do not use a single herbal prescription. Several prescriptions are used in stages, which means you have to recognize a plateau and change the prescription when it comes.
And our treatment goal is not “fast” but “certain.” As the saying goes, you tap even a stone bridge before crossing it. That is why treatment sometimes needs time.
Today we looked at a case of severe ulcerative colitis that had not responded to steroids or immunosuppressants.
That is all for today.
Thank you.
If you have questions about ulcerative colitis or Crohn’s disease, how to read calprotectin values, or when a prescription should be changed, please leave a comment. I read them and take them up as topics.
▶️ Watch our YouTube video on this case:
https://youtu.be/4Syc4_e1DXM
Please turn on subtitles to watch.
HanStep Korean Medicine Clinic – Inflammatory Bowel Disease Clinic
https://hanstep.co.kr/en/


Leave a comment